
GC201 Skin Ulcers Skin And Subcutaneous Lesions; Skin Cancer
Skin ulcers are open wounds with loss of epidermis and dermis due to vascular, infectious, or inflammatory causes, while skin cancers (basal cell, squamous cell, melanoma) are malignant neoplasms arising from cutaneous cells, and subcutaneous lesions include benign or malignant growths within or beneath the skin.
Skin Ulcers, Skin & Subcutaneous Lesions, and Skin Cancer
Use the lecture's own buckets first—epidermal, cystic, keratotic, melanocytic, dermal/subcutaneous, vascular, other benign, pre-malignant, and malignant—then use the keywords to identify the lesion. The coloured bands separate the categories; the behaviour label tells you how urgently to investigate it.
| Clinical image | Condition | Behaviour | Recognition keywords | What is happening? | Exam / action hook |
|---|---|---|---|---|---|
| A. Epidermal lesions | |||||
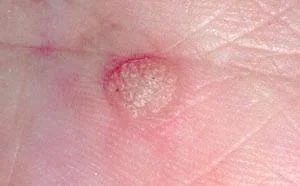 | Common wart | Benign | Rough warty top; multiple; punctate bleeding; plantar lesions painful | HPV drives keratinocyte proliferation and hyperkeratosis. | Cryotherapy/salicylic acid; interrupts normal skin lines. |
| — | Corn / callus | Benign reactive | Pressure point; corn = small painful core; callus = broad and diffuse | Repeated friction causes protective hyperkeratosis; a corn's core presses on nerves. | Remove pressure ± keratolytic; skin lines remain intact. |
| B. Cystic lesions | |||||
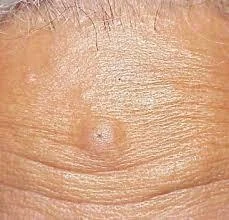 | Epidermoid cyst | Benign cyst | Attached to skin; central punctum; cheesy contents | Follicular epithelium sheds keratin—not sebum—into a true cyst. | Excise wall + punctum; multiple + osteomas/polyposis = Gardner syndrome. |
| — | Other epidermal cysts | Benign cysts | Pilar = scalp; milia = tiny facial; implantation = trauma/scar; steatocystoma = multiple | Trapped follicular/adnexal epithelium accumulates keratin or sebaceous material. | Steatocystoma is the true sebaceous cyst. |
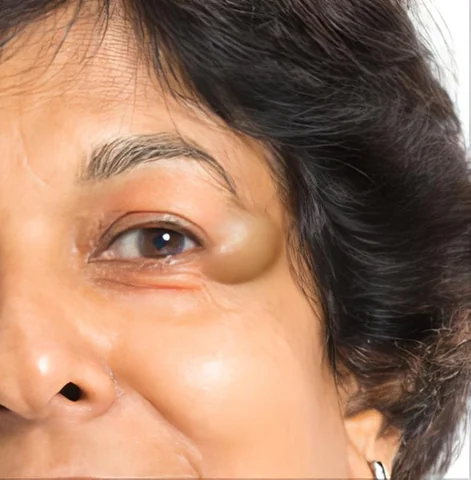 | Dermoid cyst | Benign congenital | Child; fusion line; external eyebrow, midline scalp, or mandible | Surface ectoderm trapped during embryonic fusion forms a cyst containing skin appendages. | Excise; assess deep/intracranial extension at relevant sites. |
| C. Keratotic lesions | |||||
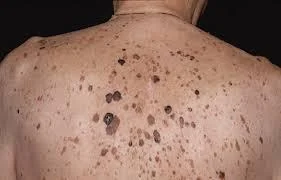 | Seborrhoeic keratosis | Benign | Waxy, brown-black, sharply defined, “stuck-on,” square-shouldered | Clonal epidermal keratinocyte proliferation produces a superficial plaque. | No malignant potential; sudden eruption = Leser-Trélat sign. |
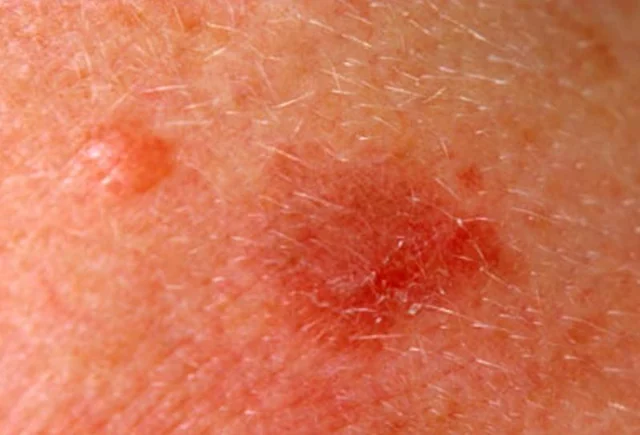 | Actinic keratosis | Pre-malignant | Sun-exposed; erythematous, dry “sandpaper” scale; felt before seen | Cumulative UV injury causes atypical keratinocytes in the epidermis. | Precursor of SCC; treat lesion or field. |
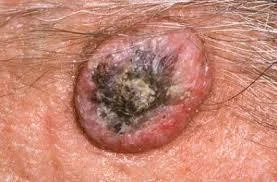 | Keratoacanthoma | SCC mimic | Rapidly growing flesh-coloured dome with central keratin crater/plug | Follicular squamous proliferation may grow, plateau, then involute but overlaps with SCC. | Excisional biopsy; do not wait for involution. |
| D. Melanocytic naevi | |||||
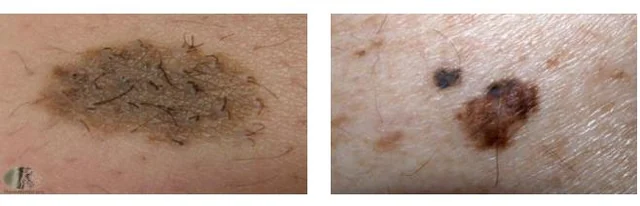 | Junctional naevus | Benign | Child/young; flat and dark | Naevus cells remain at the dermoepidermal junction. | Highest relative risk of the common naevus types, but absolute risk remains low. |
| Compound naevus | Benign | Young adult; raised with variable pigment | Naevus cells occupy both junction and dermis. | Assess any evolution or atypical features. |
| Intradermal naevus | Benign | Older adult; dome-shaped and flesh-coloured | Cells have matured into the dermis and usually lose pigment. | Very low malignant risk. |
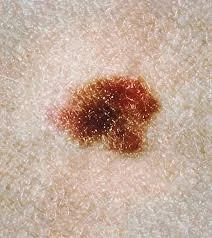 | Congenital / dysplastic naevus | Risk marker | Congenital = large, dark, hairy; dysplastic = irregular, speckled, often multiple | Atypical melanocytic proliferation or a large congenital cell burden increases melanoma susceptibility. | ABCDE + history; giant congenital/familial dysplastic patterns need surveillance. |
| E. Dermal and subcutaneous lesions | |||||
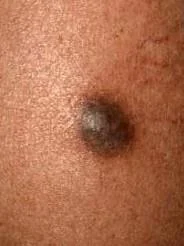 | Dermatofibroma | Benign | Firm red-brown nodule; dimple sign | Fibro-histiocytic proliferation and fibrosis tether the epidermis downward. | Distinguish from DFSP if large, growing, or atypical. |
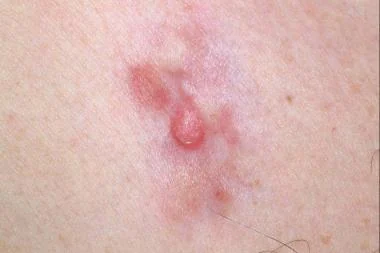 | DFSP | Locally aggressive | Slow painless indurated plaque; protuberant nodules; ill-defined | Spindle cells send tentacle-like projections through dermis and subcutis. | High local recurrence, rare metastasis → wide/Mohs-type margin control. |
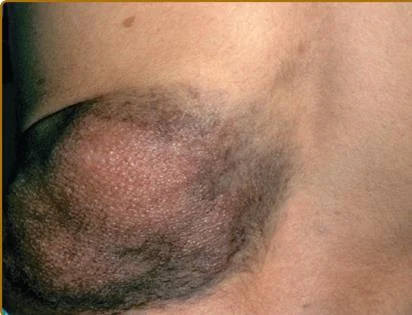 | Neurofibroma / NF1 | Usually benign | Buttonhole sign; multiple lesions + café-au-lait macules/freckling | Nerve-sheath elements proliferate along peripheral nerves. | Plexiform lesion suggests NF1 and carries malignant transformation risk. |
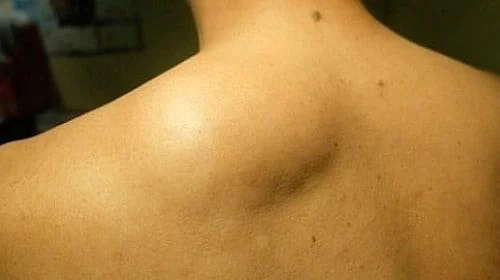 | Lipoma | Benign | Soft, lobulated, mobile; positive slip sign | Mature adipocytes form a thinly encapsulated subcutaneous mass. | Deep, painful, firm, rapidly growing, or >5 cm → image/biopsy for sarcoma. |
| F. Vascular lesions | |||||
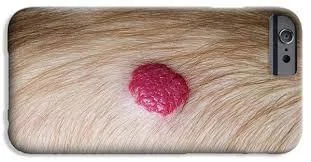 | Infantile haemangioma | Benign tumour | Appears after birth; bright red; proliferates → plateaus → involutes | True endothelial proliferation is followed by apoptosis and involution. | Observe most; propranolol if function-threatening, ulcerated, or disfiguring. |
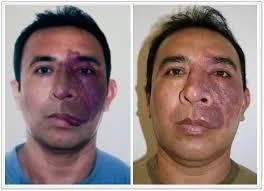 | Port-wine stain | Capillary malformation | Present at birth; flat red-purple; thickens with age; never involutes | Ectatic capillary channels grow proportionally rather than by tumour proliferation. | Pulsed-dye laser; V1 + seizures/glaucoma = Sturge-Weber. |
| — | Venous malformation / AVM | Malformation | Venous = blue, soft, compressible, slow-flow; AVM = warm, pulsatile/bruit, fast-flow | Congenital dysplastic vascular channels persist and expand. | Doppler/MRI; sclerotherapy for venous lesions, embolization ± excision for AVM. |
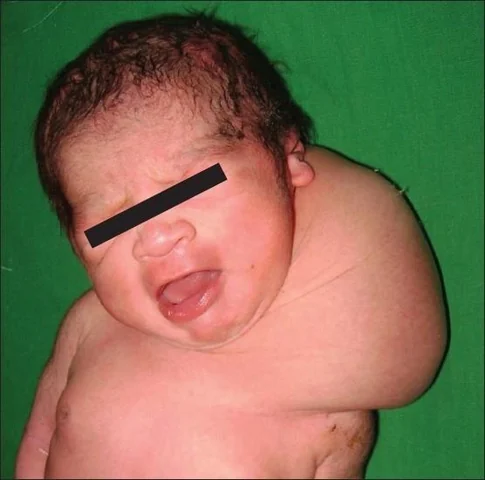 | Cystic hygroma | Lymphatic malformation | Infant; neck/axilla/groin; soft, fluctuant, brilliantly transilluminant | Sequestered lymphatic sacs fail to connect normally with the venous system. | Assess airway/extent; sclerotherapy and/or excision. |
| G. Other benign lesions | |||||
 | Skin tag | Benign | Multiple small, soft, pedunculated papules | Loose fibrovascular core is covered by normal squamous epithelium. | Reassure or remove for symptoms/cosmesis. |
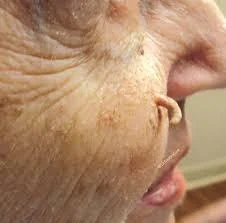 | Cutaneous horn | Descriptive sign | Conical hard keratin projection | The horn is compact keratin; the causal pathology lies at its base. | Biopsy the base—may overlie seborrhoeic keratosis, actinic keratosis, or SCC. |
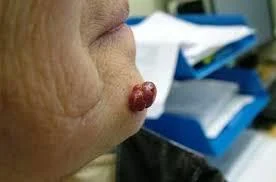 | Pyogenic granuloma | Benign reactive | Rapid red fleshy friable nodule; trauma; bleeds easily | Lobular capillary proliferation—not infection and not a true granuloma. | Remove/control base and send histology to exclude mimics. |
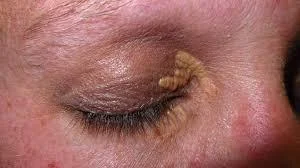 | Xanthelasma | Benign deposition | Soft yellow plaques near medial eyelids | Lipid-laden macrophages accumulate in superficial dermis. | Check fasting lipid profile. |
| — | Appendageal tumours | Usually benign | Trichoepithelioma, pilomatrixoma, syringoma, cylindroma, sebaceous adenoma | Proliferation differentiates toward hair, sebaceous, or sweat-gland structures. | Appearances overlap; histology establishes lineage. |
| — | Sebaceous naevus | Hamartoma | Congenital waxy yellow-orange scalp/face plaque; more verrucous at puberty | Mosaic hamartoma of sebaceous units and epidermis may develop secondary adnexal tumours. | Biopsy new nodularity, rapid growth, or ulceration. |
| H. Pre-malignant and in-situ conditions | |||||
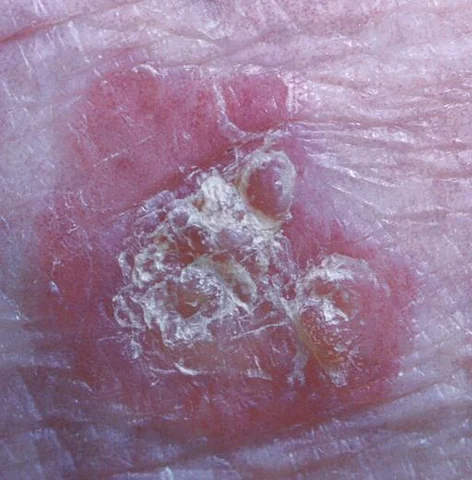 | Bowen disease | SCC in situ | Persistent irregular red-brown scaly plaque; penis = erythroplasia of Queyrat | Full-thickness epidermal dysplasia has not crossed the basement membrane. | No metastatic access until invasion; treat locally and exclude invasive SCC. |
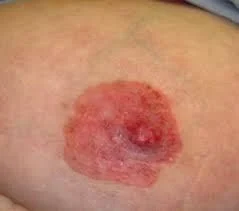 | Paget disease of nipple | Intraepidermal spread | Persistent unilateral eczematous nipple → erosion/ulceration ± breast mass | Malignant glandular cells spread from mammary ducts into nipple epidermis. | Biopsy and investigate underlying breast carcinoma. |
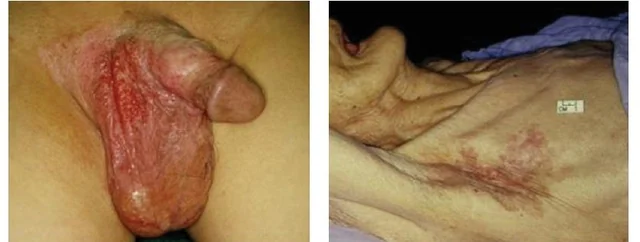 | Extramammary Paget disease | Intraepithelial adenocarcinoma | Chronic eczematous penoscrotal, vulval, perianal, or axillary plaque | Glandular malignant cells proliferate within epidermis; may accompany internal malignancy. | Biopsy, map extent, and search for associated malignancy. |
| — | High-risk skin fields | Cancer predisposition | XP, albinism, chronic radiation dermatitis, unstable scar, burn, chronic sinus | Defective UV protection/repair or repeated inflammation accumulates carcinogenic injury. | Low threshold to biopsy any changing, bleeding, or non-healing focus. |
| — | Marjolin ulcer | SCC transformation | Old burn/unstable scar/osteomyelitis sinus develops pain, growth, bleeding, or everted edge | Chronic injury and impaired immune surveillance drive an aggressive SCC. | Biopsy a changing chronic wound; metastasizes more than de novo SCC. |
| I. Major malignant skin lesions | |||||
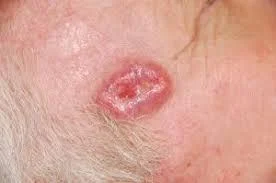 | Basal cell carcinoma | Locally malignant | Slow; pearly rolled/inverted edge; telangiectasia; rodent ulcer; often pigmented in Asians | UV-driven basal-type cells infiltrate locally but almost never metastasize. | Usually excise with 3–4 mm margin; beware morpheaform and facial danger sites. |
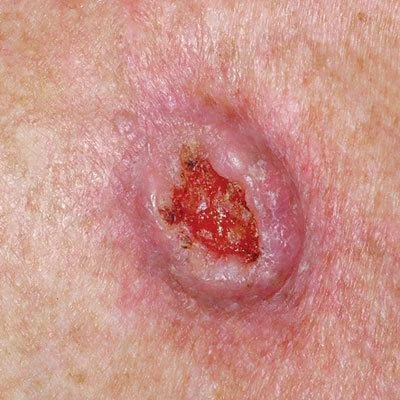 | Squamous cell carcinoma | Invasive malignant | Faster keratotic growth or ulcer; everted edge; regional nodes possible | Atypical keratinocytes cross basement membrane and access lymphatics/blood. | Excision about 6 mm–1 cm according to risk; examine regional nodes. |
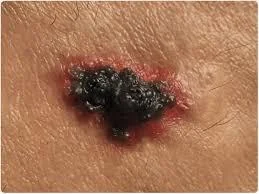 | Malignant melanoma | Highly malignant | ABCDE; evolving pigment; bleeding; satellites; acral/subungual important in Asians | Malignant melanocytes spread radially and/or vertically, then metastasize early. | Breslow thickness determines prognosis/margin; SLNB for staging when indicated. |
| J. Uncommon malignant tumours | |||||
| — | Merkel cell carcinoma | Aggressive malignant | Rapid firm painless red-violet dome; older or immunosuppressed patient | UV and Merkel-cell polyomavirus contribute to aggressive neuroendocrine cancer. | Urgent biopsy and staging; high nodal/distant metastatic risk. |
| — | Other rare cancers | Malignant | Appendageal carcinoma, sarcoma, MPNST, angiosarcoma, lymphoma, skin metastasis | Malignant cells arise from or seed non-epidermal cutaneous tissues. | Biopsy atypical aggressive lesions; do not force all cancers into BCC/SCC/melanoma. |
Clinical images are cropped directly from the corresponding lecture slides [1]. Select a thumbnail to open the full image. A dash means that the lecture did not provide a condition-specific clinical photograph.
One-line synthesis: benign lesions are usually stable, circumscribed, mobile, and non-ulcerated; malignancy is suggested by progressive growth, fixation, bleeding/ulceration, nodes, or satellites. For ulcers: rolled/inverted = BCC, everted = SCC, sloping = healing, punched-out = ischaemic/neuropathic, and undermined = destruction beneath intact skin. [1][2][7][8]
Lecturer: Dr George CC Lee, Specialist in Plastic Surgery, HKU/QMH [1]
Skin problems are common and account for ~15% of surgical OPD referrals. Patients' main concerns are: unknown nature of the lesion, fear of malignancy, and cosmetic appearance. [1]
Big Idea: This lecture is a comprehensive surgical dermatology primer covering three pillars: (1) the clinical approach to any skin/subcutaneous lump or ulcer, (2) a systematic catalogue of benign skin and subcutaneous lesions (from warts to lipomas to vascular anomalies), and (3) the three major skin cancers (BCC, SCC, melanoma) plus their pre-malignant precursors. The unifying clinical question is: "Is this benign or malignant, and what do I do about it?"
Learning Objectives (inferred from slide structure):
- Take a focused history and perform a systematic examination of skin/subcutaneous lesions
- Classify common benign lesions by layer of origin
- Recognize pre-malignant conditions and their malignant potential
- Diagnose and manage BCC, SCC, and melanoma
- Differentiate benign from malignant features clinically
- Understand vascular anomalies (tumour vs malformation)
The skin has four layers relevant to surgical pathology: epidermis (3–5 cells thick with impermeable stratum corneum), dermis (0.8–2.5 mm, fibrous and tough), hypodermis (indistinct loose fibrofatty layer containing adnexal structures), and subcutaneous fat. [1]
Why this matters: Every skin lesion can be mentally mapped to a layer of origin. Epidermis → warts, keratoses, cysts, carcinomas. Dermis → dermatofibroma, neurofibroma. Adnexal structures → sebaceous cysts, dermoid cysts, appendageal tumours. Subcutaneous → lipoma, vascular malformations.
| Layer | Key Structures | Benign Lesions | Malignant Lesions |
|---|---|---|---|
| Epidermis | Keratinocytes, melanocytes | Warts, seborrheic keratosis, keratoacanthoma, epidermoid cyst | BCC, SCC, Bowen's disease |
| Melanocytes (basal epidermis) | Melanocytes | Melanocytic naevi | Malignant melanoma |
| Dermis | Fibroblasts, vessels, nerves | Dermatofibroma, neurofibroma, pyogenic granuloma | DFSP, angiosarcoma |
| Adnexal | Hair follicle, sebaceous/sweat glands | Pilar cyst, dermoid cyst, trichoepithelioma | Appendageal carcinoma |
| Subcutaneous | Adipose tissue | Lipoma | Liposarcoma |
| Vascular | Arterioles, venules, lymphatics | Infantile haemangioma, vascular malformations | Angiosarcoma, Kaposi sarcoma |
Slide-Based Classification of Skin Lesions by Layer of Origin
The lecture also presents a six-group classification mapped directly to the skin cross-section [1]:
| Group | Layer | Benign | Pre-malignant / Malignant |
|---|---|---|---|
| 1. Epidermal | Epidermis | Skin tags, warts, seborrhoeic keratosis, keratoacanthoma | Solar keratosis, Bowen's disease, erythroplasia of Queyrat, SCC, BCC |
| 2. Melanotic | Basal epidermis | Benign pigmented naevi | Malignant melanoma |
| 3. Dermal | Dermis | Pyogenic granuloma, histiocytoma, keloid | Secondary carcinomas, Kaposi's sarcoma |
| 4. Appendageal | Skin appendages | Epidermoid cyst, dermoid cyst, pilonidal sinus, benign appendage tumours | — |
| 5. Hypodermal / deeper | Hypodermis + deeper | Lipoma, neurofibroma, neurofibromatosis, schwannoma, ganglion | Liposarcoma, sarcoma |
| 6. Vascular | Vessels | Campbell de Morgan spots, spider naevi, angiomas, glomus tumours | — |
Clinical Approach: History and Examination
Key symptoms to elicit: Onset, Progression, Pain, Discharge, Contact bleeding, Ulceration. [1]
- Onset: When did the patient first notice the lesion? Congenital lesions (dermoid cyst) vs acquired.
- Progression: Static (benign) vs rapidly enlarging (malignant or keratoacanthoma). Growth proportional to the patient → benign.
- Pain: Most benign lesions are painless. Pain may indicate infection (infected epidermoid cyst), malignancy, or neurofibroma.
- Discharge: Serous (benign cyst), purulent (infection), bloody (malignancy).
- Contact bleeding: Suggests friable tissue → malignancy or pyogenic granuloma.
- Ulceration: A lesion that ulcerates is much more likely malignant.
Also ask about:
- Number/multiplicity (multiple neurofibromas → NF; multiple epidermoid cysts → Gardner syndrome)
- Personal/family history of skin cancer or dysplastic naevi
- Sun exposure, occupational carcinogen exposure, immunosuppression
- Prior radiation therapy or chronic wounds
Signs to assess: Site, size, shape, colour, consistency, surface, border, tenderness, temperature, pulsatility, emptying, skin or deep fixation, transillumination. [1]
| Examination Component | What to Look For | Why It Matters |
|---|---|---|
| Site | Sun-exposed (BCC/SCC/actinic keratosis) vs non-exposed vs embryonic fusion line (dermoid) | Location narrows differential dramatically |
| Size | Measure in 2 dimensions with ruler | > 6mm pigmented lesion → melanoma concern |
| Shape | Dome (keratoacanthoma), pedunculated (skin tag), flat (junctional naevus) | Morphology guides diagnosis |
| Colour | Pearly (BCC), brownish-black (seborrheic keratosis/melanoma), flesh-coloured (lipoma/neurofibroma), reddish-brown (dermatofibroma) | Pigmentation patterns are discriminators |
| Consistency | Soft (lipoma), firm (dermatofibroma), hard (malignancy), cystic (epidermoid cyst) | Hard + fixed = high suspicion for malignancy |
| Surface | Smooth, rough/warty, ulcerated, keratinized | Warty → HPV/keratosis; ulcerated → malignancy |
| Border | Well-defined (benign), rolled (BCC), everted (SCC), irregular (melanoma) | Edge type is a classic exam discriminator |
| Tenderness | Present → inflammation/infection | Active infection changes management |
| Temperature | Warm → vascular or inflammatory | Cool → unlikely to be inflamed |
| Pulsatility | Expansile → arterial origin; transmitted → overlying artery | Key for vascular lesions |
| Skin fixation | Attached to skin → epidermal/dermal origin; punctum → epidermoid cyst | |
| Deep fixation | Fixed to deep structures → infiltrative malignancy | Ask patient to contract underlying muscle |
| Transillumination | Brilliantly transilluminant → cystic hygroma, clear fluid cyst | Opaque → solid or blood-filled |
| Slip sign | Lump slips away from finger → lipoma | Classic clinical sign |
| Regional lymph nodes | Enlarged → possible metastatic spread | Always palpate if malignancy suspected |
For ulcers, describe: Base (granulation tissue/slough/fascia/muscle/bone), Edge (sloping = healing; punched out; undermined; rolled = BCC; everted = SCC), Discharge (serous/sanguinous/purulent). [7][8]
Edge of Ulcer = Classic Exam Discriminator
Rolled edge → BCC (cells pile up at the periphery because they grow slowly and don't invade deeply). Everted edge → SCC (rapidly proliferating cells push outward). Sloping edge → healing ulcer. Punched-out → ischaemic/neuropathic. Undermined → TB/pressure ulcer.
Management options based on differential diagnosis: Observation/reassurance, Ablation (cauterization, laser), Excisional biopsy, Incisional biopsy ± definitive procedure, Wide excision ± reconstruction, Topical therapy, Radiotherapy, Chemotherapy/Immunotherapy. [1]
The choice depends on:
- Likelihood of malignancy → If uncertain, biopsy first
- Location → Face/cosmetically sensitive areas may need Mohs or reconstruction
- Patient fitness → RT for elderly/unfit patients
- Lesion characteristics → Superficial/multiple lesions → topical 5-FU or cryotherapy
The Occult Systemic Problem
A skin lesion may represent an occult systemic problem (e.g. Leser-Trélat sign — sudden eruption of multiple seborrheic keratoses indicating underlying visceral malignancy, classically GI adenocarcinoma). [1] Don't forget to think beyond the skin.
Benign Skin & Subcutaneous Lesions (Detailed Catalogue)
A. Epidermal Lesions
Multiple papular skin-coloured lesions with irregular thickened keratinized (warty) top. Caused by HPV. Contagious, therefore often multiple. Plantar warts = flattened and painful. Genital warts = soft and fleshy (condylomata acuminata). [1]
- Why warty? HPV infects keratinocytes → stimulates excessive keratinization → hyperkeratotic surface
- Treatment: Cryotherapy, salicylic acid, curettage. Spontaneous resolution possible (immune-mediated clearance)
Massive thickening of the stratum corneum due to chronic trauma/irritation. Corn = smaller, well-defined margin, square-shouldered. Callous = larger, more diffuse, slope-shouldered. Treatment: removal of irritation, curettage, or keratolytic agent (10–20% salicylic acid). [1]
- Why the distinction? Corn has a central core of hard keratin that presses on nerve endings → painful. Callous is more diffuse without a core → less painful.
- DDx corn vs plantar wart: Wart interrupts skin lines and has punctate bleeding on paring; corn preserves skin lines.
Pearly penile papules (normal anatomical variant — small pale papules at the coronal margin of the glans) should be distinguished from genital warts. [1]
B. Cystic Lesions
True cyst with epithelial lining, ?hair follicle origin. Spherical, attached to skin (punctum). Contains cheesy keratin material, NOT sebum. May get infected. Multiple → Gardner's syndrome (associated with osteoma, fibromas, intestinal fibromatoses, lipomas, leiomyomas, and polyposis coli). Treatment: Excision. [1]
High Yield: Epidermoid Cyst ≠ Sebaceous Cyst
Despite being colloquially called "sebaceous cyst," epidermoid cysts contain keratin, not sebum. The true sebaceous cyst is steatocystoma multiplex (rare). This is a classic exam trap. The punctum (visible pore on skin surface) is the pathognomonic clinical sign and must be included in excision to prevent recurrence. [1]
- Gardner syndrome = FAP variant with epidermoid cysts + osteomas + fibromas + desmoid tumours + colonic polyps → screen for colorectal cancer
Implantation dermoid: epidermal fragment driven into dermis by penetrating injury; tensely cystic; history of trauma or scar. Milia: small 1–2mm epidermal cysts on face. Pilar cyst (trichilemmal cyst/wen): slow-growing firm cyst on scalp. Steatocystoma multiplex: true sebaceous cyst! [1]
Congenital cystic lesion growing slowly. Occurs at embryonic fusion line regions (midline scalp, external angle of eye, lower mandible). Contains keratin, hair, sebaceous glands, etc. Treatment: Excision. [1]
- Why fusion lines? During embryonic development, surface ectoderm gets trapped beneath as fusion occurs → forms a cyst containing fully differentiated ectodermal elements
- External angular dermoid (lateral eyebrow) is the most common site in children → must exclude intracranial extension before excision
C. Keratotic Lesions
Common in elderly. Brownish-black, raised, well-marginated. Plaque-like papules, 'stuck-on', square-shouldered. Feels waxy and irregular. Proliferation of basal cells of epidermis. Treatment: cryotherapy, curettage, shaving, excision. [1]
- 'Stuck-on' appearance is the classic descriptor — looks like it was glued onto the skin surface
- Benign — no malignant potential (but sudden eruption of many = Leser-Trélat sign)
- DDx melanoma: Seborrheic keratosis can be heavily pigmented → dermoscopy helps differentiate (SK shows comedo-like openings, milia-like cysts)
Sun-damaged skin, UV-induced, on exposed parts. Dry, scaly or crusty top with erythematous base. Early lesions are flat, roughened or scaly papules which could just be palpable. Hyperkeratosis and acanthosis, PRE-MALIGNANT. Treatment: Excision; if multiple — excision, curettage, cryosurgery, 5-FU creams. [1]
Actinic Keratosis is Pre-Malignant
Actinic keratosis has a ~5–10% risk of progression to SCC if left untreated. This is the most common pre-malignant skin lesion. It appears on sun-damaged skin (face, dorsum of hands, forearms, scalp in bald men). The key clinical clue is a rough, sandpaper-like feel on palpation — "you can feel it before you see it." [1]
Dome or nodular-shaped, flesh-coloured. Central crater filled with a keratin plug. Natural history: rapid growth for a few weeks → static for a few months → involution. ?Variant of SCC. Treatment: Excisional biopsy. [1]
- Why excise if it involutes? Because it is clinically and sometimes histologically indistinguishable from well-differentiated SCC. You cannot safely observe and wait.
- Key differentiator from SCC: Keratoacanthoma has a characteristic rapid growth then spontaneous regression pattern; SCC does not involute.
D. Melanocytic Naevi
Naevi = developmental abnormalities with hyperplasia of incompletely differentiated tissue elements. Types: Melanocytic naevus (Mole), Strawberry naevus (Infantile haemangioma), Sebaceous naevus (Naevus of Jadassohn). [1]
Location of naevus cells determines type:
- Junctional: in child, flat, darkly pigmented (naevus cells at dermoepidermal junction)
- Compound: in younger adult, raised, variable pigmentation (cells at junction + dermis)
- Intradermal: in older adult, dome-shaped, flesh-coloured (cells entirely in dermis)
- Congenital: big, hairy, dark, raised, thick [1]
| Type | Age | Appearance | Location of Cells | Malignant Risk |
|---|---|---|---|---|
| Junctional | Children | Flat, dark | Dermoepidermal junction | Low (but highest of the three) |
| Compound | Young adults | Raised, variably pigmented | Junction + dermis | Low |
| Intradermal | Older adults | Dome-shaped, flesh-coloured | Dermis only | Very low |
| Congenital (giant) | Birth | Large, hairy, dark | Full thickness | ~5% lifetime risk of melanoma |
| Dysplastic | Any age | Irregular border, speckled | Variable | Up to 400× lifetime risk (familial) |
What the layer diagram shows: junctional nest sitting on the dermoepidermal junction → compound spanning junction + dermis → intradermal nest wholly in the dermis — the histology behind flat/dark vs raised vs dome-shaped flesh-coloured. [1]
Other melanocytic naevus variants mentioned in the lecture include blue naevus, Spitz naevus, and halo naevus. [1]
Moles are very common and benign. Risk of malignant change is very small EXCEPT in: Dysplastic naevus (especially with family/personal history), Giant congenital melanocytic naevus ('Bathing trunk' — life-long surveillance), > 50 naevi, > 2mm size. DDx: Melanoma, BCC, seborrheic keratosis. When in doubt: biopsy. [1]
Uncommon in Asians, usually multiple, occasionally solitary. Two major groups: Sporadic (Caucasians, fair skin, poorly tanned, excessive sunlight) and Familial (Dysplastic naevus syndrome, runs in families, uncommon, up to 400× lifetime risk of malignant change). Irregular border and speckled pigmentations. [1]
E. Dermal/Subcutaneous Lesions
Firm skin nodule, 0.5–3 cm. History of trauma or insect bite. Deep reddish-brown. ?Histiocytic origin. Fibrosis + vascularity + iron pigmentation. DDx: dermatofibrosarcoma protuberans. [1]
- Dimple sign (Fitzpatrick sign): Pinching the lesion causes it to dimple inward because the lesion is tethered to overlying epidermis — classic exam sign [8]
Locally aggressive. Painless, indurated plaque with irregular nodules. Skin-coloured, border not well defined. ?Fibroblastic origin. Infiltrative histologically with cords/nests of cells invading adjacent soft tissue. Prone to local recurrence, seldom metastasizes. Treatment: Wide excisional margin ± RT. [1]
Solitary: subcutaneous, tender, firm, mobile. Multiple: sessile or pedunculated, skin-coloured or brownish, well-circumscribed. From supporting fibroblasts of peripheral nerves. [1]
- Buttonhole sign: Can be pushed through a defect in the skin — pathognomonic
Autosomal dominant: NF-1, NF-2. Multiple lesions of different sizes, café-au-lait pigmentations, acoustic neuroma. Deformities/disfigurement, possible malignant transformation. Plexiform NF: skin thickened and folded, myxofibromatous degeneration. [1]
- NF-1 diagnostic criteria (≥2 of): ≥6 café-au-lait macules (> 5mm pre-pubertal, > 15mm post-pubertal), ≥2 neurofibromas or 1 plexiform NF, axillary/inguinal freckling, optic glioma, ≥2 Lisch nodules, distinctive bony lesion, first-degree relative with NF-1
Subcutaneous lump/mass, 1 to > 20 cm. Diffuse vs well-defined lobulated mass. Matured fat cells in thin fibrous capsule. Big lipoma may be soft and fluctuant. Treatment: Excision, liposuction. Pain, rapidly enlarging, skin changes, firm consistency may indicate malignancy. [1]
F. Vascular Lesions
Vascular tumour: rapid proliferating vascular endothelium. Vascular malformation: congenital abnormal vascular anatomy and morphology. [1]
This is the ISSVA classification — the key distinction is that tumours grow by cellular proliferation (and can involute) while malformations are structural errors (present at birth, grow proportionally, never involute).
| Feature | Haemangioma (Tumour) | Vascular Malformation |
|---|---|---|
| Present at birth | Usually not present at birth | Present at birth (may not be clinically apparent) |
| Growth | Rapidly increases in size | Grows in proportion to body size |
| Involution | Involutes | Does not involute (can degenerate; AVM can hypertrophy) |
| Sex ratio | F:M = 3:1 | No sex predilection |
| Location | 60% head and neck | Variable |
| Epidemiology | Most common tumour of infancy | — |
Bright red haemangioma in baby. Usually appears shortly after birth, rapidly grows for a few weeks to months → becomes static → involution starts. Residual redundant skin or scar is common. Treatment: Observation, steroid, beta-blocker, laser, excision. [1]
- Propranolol is now first-line medical therapy (replaced steroids) — mechanism: vasoconstriction + inhibition of angiogenesis + induction of apoptosis
- When to treat: Threatening vital structures (airway, visual axis), ulcerating, disfiguring
Critical Compromise Indications for Treatment
Intrinsic complications: bleeding, ulceration, Kasabach–Merritt syndrome (thrombocytopenia — note: associated with kaposiform haemangioendothelioma, not common infantile haemangioma). [1]
Extrinsic compromise: upper eyelid involvement → deprivation amblyopia and failure to develop binocular vision, corneal distortion and astigmatism; airway obstruction. [1]
Fast flow vs Slow flow. Diagnosis by history and physical exam. Adjuncts: USG, MRI, Angiography. [1]
| Type | Flow | Example | Treatment |
|---|---|---|---|
| Arterial | Fast | AVM | Pre-op embolization ± complete excision |
| Schobinger staging: I = blue-skin blush; II = mass with bruit/thrill; III = ulceration, bleeding, pain; IV = heart failure | |||
| Venous | Slow | Venous malformation | Debulking, sclerotherapy |
| Capillary | Slow | Port-wine stain | Laser (pulsed dye) |
| Lymphatic | Slow | Cystic hygroma (macrocystic or microcystic), primary lymphoedema | Excision, sclerotherapy |
| Combination | Mixed | Klippel-Trenaunay, Parkes-Weber | Multidisciplinary |
Capillary malformation. Present at birth, often on face/scalp. Flat or slightly elevated, reddish-blue to purplish. With advancing age becomes thicker and nodular. Associated with intracranial haemangioma. DDx: Sturge-Weber Syndrome. [1]
- Sturge-Weber = port-wine stain in V1 distribution + ipsilateral leptomeningeal angioma + glaucoma + seizures + "tram-track" intracranial calcifications
Collection of lymphatic sacs containing lymph. Failure of fusion of lymphatic channels. Most present at birth. Usually root of neck, axilla, groin. Soft, fluctuant, and markedly transilluminating. Treatment: Excision, sclerotherapy. [1]
- Brilliant transillumination is the classic finding — distinguishes from other neck masses in neonates
- Associated with Turner syndrome (45,X) and other chromosomal abnormalities
G. Other Benign Lesions
Often multiple, 1–5 mm. Loose connective tissue core with normal covering squamous epithelium (pigmented or keratinized). Treatment: Excision, laser. [1]
Descriptive term — any protuberant horny skin growth. Usually conical projection of keratinized material. Pathologically may be actinic keratosis (with or without underlying SCC), seborrheic keratosis, or SCC. [1]
Cutaneous Horn = Always Biopsy the Base
The horn itself is just keratin. The pathology is at the base — which may be benign (seborrheic keratosis) or malignant (SCC). Always excise and send for histology. [1]
Induced by trauma. Red, fleshy, spherical nodule. Rapid and excessive growth of granulation tissue rich in blood vessels and inflammatory cells. Ulcerate and bleed easily. Treatment: Excision, curettage and diathermy of base. [1]
- Misnomer: Not pyogenic (not pus-producing) and not a true granuloma — it's a lobular capillary haemangioma
- DDx: Amelanotic melanoma, SCC, Kaposi sarcoma → always send for histology
Deposition of lipid-laden macrophages in superficial dermis. Soft, flat-topped yellow papules, may coalesce. Usually starts at upper eyelid near medial canthus. About 1/3 of patients have hyperlipoproteinaemia. Treatment: Excision, laser. [1]
- Clinical pearl: Check fasting lipid profile in all patients with xanthelasma
Hair follicle: trichofolliculoma, trichoepithelioma, pilomatrixoma, trichilemmoma. Sebaceous gland: sebaceous adenoma. Sweat gland: cylindroma, syringoma. Some have typical appearance; otherwise diagnosis confirmed on histological exam. [1]
- Hamartoma of sebaceous glands with epidermal hyperplasia
- Typically on scalp/face, appears waxy/yellowish in childhood
- 10–15% risk of malignant transformation → classically BCC [2]
Pre-Malignant Skin Conditions
Pre-malignant conditions: Bowen's disease, Paget's disease of nipple, Xeroderma pigmentosa, Albinism, Chronic unstable scar or destruction of skin, Chronic radiation dermatitis, Burn scar/chronic osteomyelitis, Actinic keratosis. [1]
Dysplastic cells confined to basal lamina. Thickened, reddish-brown, scaly patch with irregular border. In penis = erythroplasia of Queyrat (velvety-red plaque). Treatment: Excision, radiotherapy, topical 5-FU, cryotherapy, photodynamic therapy. [1]
- Why "in-situ"? The abnormal cells have NOT breached the basement membrane → no invasion → no metastatic potential yet
- Risk of progression to invasive SCC: ~3–5% if untreated
Paget cells arise from mammary ducts to nipple epidermis. Erythema and eczematous lesion of the nipple → erosion and ulceration. 50–60 years old. 97% has underlying breast carcinoma, about half present with a breast mass. Diagnosis: Incisional biopsy. Treat underlying CA Breast. [1]
Paget's Disease of Nipple = Breast Cancer Until Proven Otherwise
97% of nipple Paget's has an underlying breast carcinoma. Any persistent eczematous change of the nipple that doesn't respond to topical treatment needs biopsy. This is a classic exam scenario. [1]
Peno-scrotal/axillary areas. Intraepithelial adenocarcinoma. Underlying malignancy (e.g. Prostate, Colon). Treatment: Wide excision. [1]
Skin Cancers
| BCC | SCC | Melanoma | |
|---|---|---|---|
| Prevalence | ~75% of skin cancers | ~20% | ~5% |
| Aggressiveness | Least | Intermediate | Most |
| Metastasis | Very rare | Lymphatic + haematogenous | Lymphatic + haematogenous (early) |
Due to excessive sunlight (UV) exposure. On face/scalp/neck/dorsum of hands/forearms. Also in patients with XP, albinism, Gorlin syndrome (naevoid BCC syndrome), and sebaceous naevus. Multiple lesions common. [1]
Originates from basal epidermal cells (?pilosebaceous unit), slow growing. Seldom spreads to regional LN or by blood. Clinical types: pigmented (common in Orientals), nodular(-ulcerative), superficial, cystic, morpheaform (sclerosing). Typical ulcer with rolled edge, 'cystic lesion' with pearly white edge and telangiectasia. [1]
Most lesions are well localized. Treatment: Excision with margins (3–4 mm) ± reconstruction, radiotherapy, 5-FU cream. Cryotherapy, cauterization, or electrodesiccation should be used with much caution. Beware of lesions: post-op or RT recurrence, at medial canthus, peri-alar or pre-auricular region, the morphea type. [1]
BCC Key Points for Exams
Clinical recognition:
- Rolled, pearly edge with telangiectasia (Caucasians)
- Pigmented BCC is common in Orientals/Hong Kong [1][2]
- Central ulceration ("rodent ulcer")
- Slow growing, almost never metastasizes
Why medial canthus/peri-alar/pre-auricular are dangerous: These areas correspond to embryonic fusion planes where BCC can track deeply along tissue planes → incomplete excision → aggressive local destruction.
Morpheaform (sclerosing) BCC: The most dangerous subtype — ill-defined, scar-like, no classic rolled edge → difficult to assess margins clinically → higher recurrence rate.
Excision margins: 3–4 mm for well-defined BCC; larger (4–6 mm) for morpheic or > 2cm [1][2]
Gorlin Syndrome (Naevoid BCC Syndrome): Autosomal dominant, PTCH1 gene mutation → multiple BCCs from young age + jaw keratocysts + skeletal anomalies + calcified falx cerebri.
Mostly from excessive sunlight (UV), may develop from actinic keratosis. Other causes: carcinogens (RT, arsenic, chromium, soot, tar), chronic non-healing wounds, unstable scars. Congenital: XP and albinism. Immunosuppression: diseases or therapy. [1]
Irregular ulcer with everted edge or exophytic growth. Evidence of sun-damaged skin lesions. Metastasizes by lymphatic and haematogenous route. Treatment: Wide excision (6mm–1cm) ± reconstruction, Regional LN dissection for LN metastases. [1]
| Feature | BCC | SCC |
|---|---|---|
| Edge | Rolled | Everted |
| Growth | Slow | Faster |
| Metastasis | Almost never | Yes (lymphatic + blood) |
| Excision margin | 3–4 mm | 6 mm – 1 cm |
| Pre-malignant lesion | Sebaceous naevus | Actinic keratosis, Bowen's disease |
| Typical appearance | Pearly nodule, telangiectasia | Irregular ulcer, keratinized surface |
| Pigmented (HK) | ~80% | Uncommon |
SCC from Chronic Wounds = Marjolin's Ulcer
SCC arising in chronic non-healing wounds (venous ulcers, burn scars, osteomyelitis sinuses) is called a Marjolin's ulcer. It has worse prognosis than de novo SCC because it arises in an already immunologically compromised tissue bed. Any chronic ulcer that changes character (new pain, new growth, raised edges) needs biopsy. [1][2][8]
Malignant Melanoma
Malignant tumour of melanocytes (mesodermal), normally located in basal layer of epidermis. Cutaneous ones induced by sunlight (UV). Other sites: mucous lining, choroid of eye, meninges, soft tissues (amelanotic melanoma). Prone to lymphatic and haematogenous metastasis. [1]
Most are darkly pigmented lesions. Recent onset or change in pigmentation of pre-existing lesion, irregular appearance. Increase in size, bleeding, loss of hair. Satellite or in-transit lesions. Regional and distant LNs. [1]
| Letter | Feature | Why |
|---|---|---|
| A | Asymmetry | Irregular growth pattern |
| B | Border irregular | Poorly defined, notched |
| C | Colour variegated | Multiple shades (brown, black, red, white, blue) |
| D | Diameter > 6mm | Larger lesions more concerning |
| E | Evolving | Any change in size, shape, colour, or new symptoms |
Superficial spreading, Nodular (most aggressive), Lentigo maligna melanoma (least aggressive), Acral lentiginous melanoma, Subungual melanoma. [1]
| Subtype | Frequency | Key Features |
|---|---|---|
| Superficial spreading | MC worldwide | Radial growth phase → vertical; flat with irregular borders |
| Nodular | 2nd MC | Most aggressive; vertical growth from start; raised, dome-shaped |
| Lentigo maligna | Elderly, sun-damaged | Least aggressive; slow radial growth on face; flat, irregular |
| Acral lentiginous | MC in HK/Asians (~52%) | Palms, soles, nail beds; NOT related to UV |
| Subungual | Subset of acral | Under nail; Hutchinson's sign (pigment extending to nail fold) |
Acral Lentiginous Melanoma is MC in Hong Kong
In Asian populations, acral lentiginous melanoma is the most common subtype (~52% in HK), occurring on palms, soles, and nail beds. This is NOT UV-related, so don't dismiss melanoma just because a patient "doesn't sunbathe." Hutchinson's sign (periungual pigmentation) is pathognomonic for subungual melanoma. [2]
Breslow scale (thickness) and Clark's level of invasion both correlate with LN metastases and survival. Breslow scale is more favoured for less observer variability. [1]
| Breslow Thickness (mm) | 5-Year Survival (%) |
|---|---|
| < 0.76 | 98 |
| 0.76–1.50 | 90 |
| 1.51–4.0 | 70 |
| > 4.0 | < 50 |
| Clark's Level | Depth |
|---|---|
| I | Above basement membrane (in-situ) |
| II | Papillary dermis |
| III | Papillary-reticular dermis junction |
| IV | Reticular dermis |
| V | Subcutaneous fat |
The thinner the lesion, the better the prognosis. Surgery is the only treatment method for potential cure. Excision margin depends on Breslow's thickness, range from 1–2 cm. Sentinel lymph node biopsy in intermediate thickness tumour carries prognostic information and facilitates staging. Regional lymph node dissection improves nodal disease control but NOT survival. [1]
| Breslow Thickness | Excision Margin |
|---|---|
| In-situ | 0.5 cm |
| ≤1 mm | 1 cm |
| 1.01–2 mm | 1–2 cm |
| 2.01–4 mm | 2 cm |
| > 4 mm | 2 cm |
Block dissection for LN metastasis if no distant metastases. ?Role of elective block dissection in intermediate thickness tumour. Hyperthermia and isolated limb perfusion for in-transit metastases in specialized centres. Systemic chemotherapy not useful. Immunotherapy. [1]
Key Melanoma Management Principles
- SLNB is for staging/prognosis in intermediate thickness (1–4 mm) — it does NOT improve survival but guides adjuvant therapy decisions.
- Regional LN dissection = for clinically/pathologically positive nodes; improves local control but NOT overall survival.
- Immunotherapy (checkpoint inhibitors: anti-PD-1, anti-CTLA-4) has revolutionized metastatic melanoma treatment.
- Systemic chemotherapy (e.g., dacarbazine) has poor response rates and is NOT considered useful per the lecture. [1]
Merkel cell carcinoma, Skin appendageal carcinoma, Sarcomas, Malignant nerve sheath tumour, Angiosarcoma, Lymphoma, Metastatic tumour. [1]
- Merkel cell carcinoma: Rare neuroendocrine tumour; rapidly growing, firm, non-tender, dome-shaped nodule; aggressive with high metastatic potential; UV and polyomavirus associated
Benign: In young patients (except melanoma and sarcoma), remain static or grow in proportion, do not ulcerate or bleed, well-defined regular border, can be raised or flat, no enlarged regional LNs. [1]
Malignant: More common in elderly, grow in size, arise from pre-existing lesions (naevus, scar), do ulcerate or bleed, irregular or poorly defined border, raised, enlarged regional LNs, satellite lesions. [1]
| Feature | Benign | Malignant |
|---|---|---|
| Age | Young (exceptions: melanoma, sarcoma) | Elderly |
| Growth | Static or proportional | Progressive enlargement |
| Ulceration/bleeding | No | Yes |
| Border | Well-defined, regular | Irregular, poorly defined |
| Regional LN | Not enlarged | May be enlarged |
| Satellite lesions | Absent | May be present |
| Pre-existing lesion | Usually de novo | May arise from naevus/scar |
Exam Intelligence
| Trap | Correct Understanding |
|---|---|
| "Sebaceous cyst contains sebum" | Epidermoid cyst contains keratin, NOT sebum |
| "BCC metastasizes" | BCC almost never metastasizes; locally destructive only |
| "All melanomas are UV-related" | Acral lentiginous melanoma (MC in Asians) is NOT UV-related |
| "LN dissection improves survival in melanoma" | Improves nodal disease control but NOT overall survival |
| "Keratoacanthoma is benign and can be observed" | Clinically indistinguishable from SCC → always excise |
| "Port wine stain = infantile haemangioma" | Port wine stain is a capillary malformation (never involutes); infantile haemangioma is a tumour (involutes) |
| "Cutaneous horn is a diagnosis" | It is a descriptive term — must biopsy base to determine pathology |
| "Rolled edge = SCC" | Rolled edge = BCC; Everted edge = SCC |
| "Superficial spreading melanoma is MC in HK" | Acral lentiginous melanoma is MC in HK (~52%) |
| Association | Significance |
|---|---|
| Multiple epidermoid cysts + osteomas + colonic polyps | Gardner syndrome → screen for FAP |
| Sudden eruption of seborrheic keratoses | Leser-Trélat sign → underlying visceral malignancy |
| Café-au-lait spots + multiple neurofibromas | NF-1 |
| Port wine stain V1 + seizures + glaucoma | Sturge-Weber syndrome |
| Multiple BCCs in young patient + jaw keratocysts | Gorlin syndrome |
| Paget's disease of nipple | 97% underlying breast carcinoma |
| Extramammary Paget's | Underlying prostate/colon carcinoma |
| Xeroderma pigmentosa | Defective DNA repair → early skin cancers (BCC, SCC, melanoma) |
- Ulcer causes by frequency [7]: Venous insufficiency (60%) > Arterial insufficiency (20%) > Rapidly growing tumours/malignancy (1%) > Neuropathy/trauma (1%) > Chronic infection. A Marjolin's ulcer (SCC in chronic wound) bridges the overlap between chronic wounds and malignancy.
- Examination of lumps and bumps [7][8]: The detailed OSCE framework for examining skin lumps (inspection → palpation → special tests → regional LN) aligns directly with this lecture's examination approach.
- Dermatology CFB lectures [10][11]: Provide complementary classification of skin lesion morphology (macule, papule, plaque, nodule, vesicle, bulla, pustule, abscess, cyst, ulcer) — useful for describing lesions in OSCE.
High Yield Summary
-
Epidermoid cyst
- contains KERATIN not sebum; punctum is pathognomonic; multiple → think Gardner syndrome.
-
Actinic keratosis
- is the most common pre-malignant skin lesion → can progress to SCC.
-
Bowen's disease
- = SCC-in-situ (dysplastic cells confined above basement membrane); penile form = erythroplasia of Queyrat.
-
Paget's disease of nipple
- = 97% underlying breast carcinoma.
-
BCC
- Rolled edge, pearly, telangiectasia; pigmented in Orientals; almost NEVER metastasizes; excise with 3–4 mm margin. Beware morpheaform type and dangerous locations (medial canthus, peri-alar, pre-auricular).
-
SCC
- Everted edge; arises from actinic keratosis/Bowen's/chronic wounds (Marjolin's); DOES metastasize; excise with 6 mm–1 cm margin + LN dissection if indicated.
-
Melanoma
- ABCDE rule; Breslow thickness is the key prognostic factor; acral lentiginous is MC in HK/Asians; excision margin 1–2 cm based on thickness; SLNB for intermediate tumours (prognostic, not therapeutic); LN dissection controls nodal disease but does NOT improve survival; immunotherapy for advanced disease.
-
Vascular anomalies
- ISSVA classification — Tumour (proliferating, involutes) vs Malformation (structural, never involutes). Infantile haemangioma → propranolol. Port wine stain → laser; think Sturge-Weber.
-
Benign vs Malignant features
- Static/proportional growth, well-defined borders, no ulceration/bleeding, no LN = benign. Growing, ulcerating, irregular borders, LN involvement, satellite lesions = malignant.
-
Cutaneous horn
- Always biopsy the base — it may be SCC.
Active Recall - Lecture Notes
[1] Lecture slides: GC 201. Skin ulcers skin and subcutaneous lesions; skin cancer.pdf [2] Senior notes: Maksim Surgery Notes.pdf (Section 4.5 Skin cancers, Vascular lesions) [3] Past papers: 2021 Fourth Summative Assessment MCQ.pdf (EMQ Section II, Q6-Q10) [4] Past papers: 2021 Fourth Summative SAQ.pdf (Q7) [5] Past papers: 2023 Fourth Summative MCQ.pdf (Q66) [6] Past papers: 2025 Fourth Summative MCQ.pdf (EMQ Section V, Q21-Q25) [7] Senior notes: Ryan Ho Fundamentals.pdf (Examination of lumps and bumps, Causes of ulcers) [8] Senior notes: Ryan Ho Rheumatology.pdf (Sections 5-6, Benign and Malignant Skin Lesions) [10] Lecture slides: CFB (MED08) Dermatology (I).pdf [11] Lecture slides: CFB (MED09) Dermatology (II).pdf [12] Lecture slides: Clinical Demonstration_Skin.pdf [13] Senior notes: MBBS Final MB (Surgery) (Felix PY Lai).pdf (Section II, Skin lesions)
GC200 RUQ Pain, Jaundice And Fever Cholecytitis And Cholangitis Imaging Of GI System
Imaging of the GI system in the context of cholecystitis and cholangitis involves the use of ultrasound, CT, MRCP, and HIDA scanning to evaluate right upper quadrant pain, jaundice, and fever by identifying gallstones, biliary dilation, gallbladder wall thickening, and ductal obstruction.
GC202 Surgery May Cure Your Cancer Surgical Oncology
Surgical oncology is the branch of surgery focused on the curative resection of malignant tumors, aiming to achieve complete removal of cancerous tissue with adequate margins to eliminate disease.